


Your first visit is a consultation. We review what has and hasn’t worked, your medications and your imaging, then plan the steps toward a correct diagnosis. We do not prescribe controlled substances, such as opioids, at the first visit.
Your first visit is a consultation. We review what has and hasn’t worked, your medications and your imaging, then plan the steps toward a correct diagnosis. We do not prescribe controlled substances, such as opioids, at the first visit.
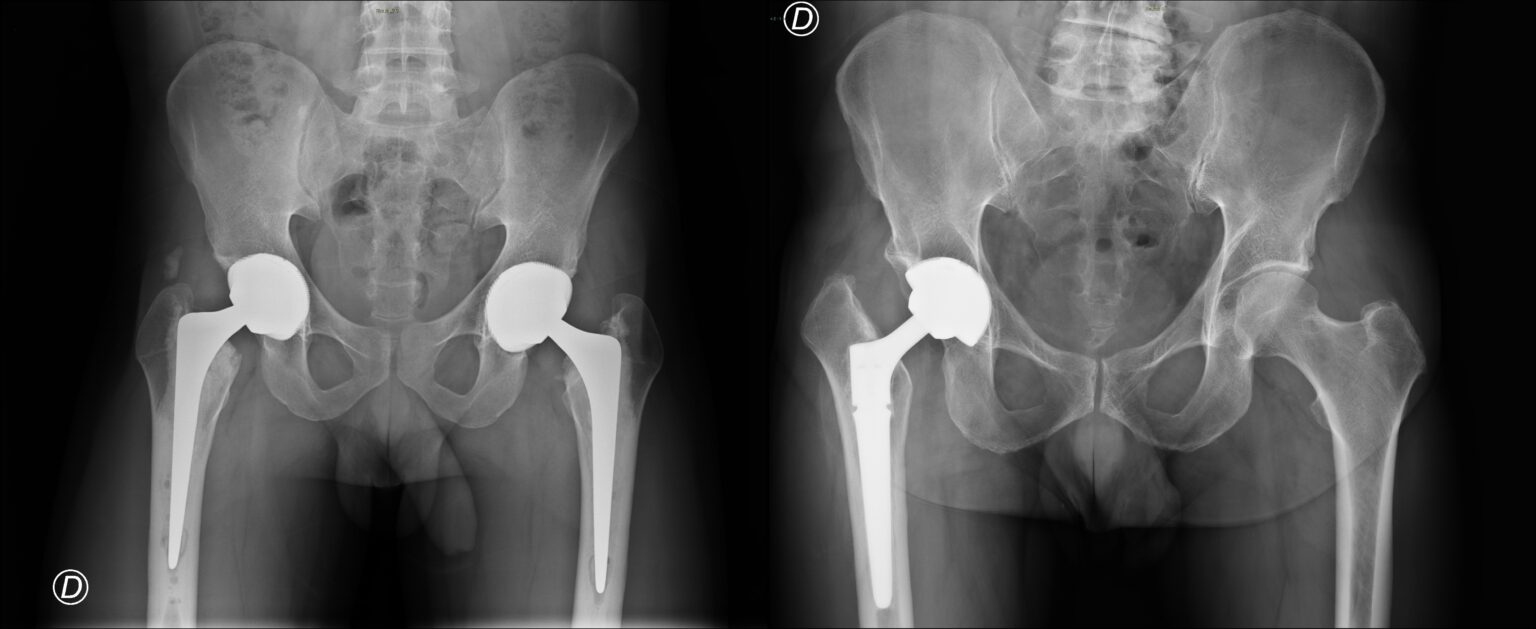
You may have been told your hip is bone on bone and that a replacement is coming. You may have already had one, and it still hurts. A scan showing wear does not prove the wear is what hurts — and a replacement that did not help usually means the pain was never coming from the joint in the first place. We establish where it is actually coming from before anything is treated.
Wear shows up on imaging in most people past a certain age, whether or not it hurts. So a scan showing arthritis in your hip does not, on its own, tell anyone that the arthritis is what you are feeling. Plenty of people have a hip that looks worse than yours on film and no pain at all.
We use selective nerve blocks to find out. A numbing injection placed at one specific place, to establish whether that is the source. If the pain goes, we have found it. If it does not, we have learned something equally useful.
Finding the correct nerve is what we specialize in. The right cause, then the right treatment, for the right problem — and in that order. Every other order is a guess wearing a procedure’s name.
Hip, spine or SI joint? 1 the hip · 2 the low back · 3 the SI joint. Back Pain →
X-rays of the pelvis after hip replacement.
Arthritis on a hip X-ray is only one possible answer. These are the other things most often behind hip pain. Tap one to see what it feels like and how it is told apart.
Coming from somewhere else
Pain in the buttock or the back of the hip together with low back pain, sometimes burning down the leg.
Examination of the back, and the MRI.
Pain low at the back of the hip or in the buttock.
Tenderness over the joint, and an image-guided numbing injection into the joint.
Burning, tingling or numbness on the outer thigh.
A numbing block of the nerve where it enters the thigh. If the pain goes, the nerve is the source.
A numbing block first, which both makes the diagnosis and settles the pain for a time; then a seven-day peripheral nerve stimulator trial. If the trial works, that is the treatment.
Pain at the front of the hip that is really coming from the belly or pelvis.
An examination of the abdomen.
We refer you out.
Around the hip
Pain on the outside of the hip, worse walking, sitting a long time, or lying on that side.
A tender bony point on the side of the hip and strength tests; an MRI or ultrasound can show a tendon tear. Usually the tendon, rarely the bursa alone.
We refer you out for physical therapy and, where needed, a surgical consultation.
Groin pain with clicking, catching or popping, worse bending or twisting.
Specific hip tests, X-rays, and an MRI. Labral tears are also found in many hips that do not hurt.
We refer you out for physical therapy and, where needed, a surgical consultation.
A sudden, painful joint. The hip is one of the joints it can affect.
Finding calcium crystals in fluid drawn from the joint.
We refer you out for physical therapy and, where needed, a surgical consultation.
Warning signs — do not wait
Deep hip pain with a limp and stiffness. More likely after steroid use, heavy drinking or smoking.
An MRI. Early X-rays can be normal.
We refer you out for physical therapy and, where needed, a surgical consultation.
Groin or hip pain with walking or standing, often after a lot of activity.
An MRI. Early X-rays are often normal.
We refer you out for physical therapy and, where needed, a surgical consultation.
Not sure which one fits? That is what the first visit is for. We test before we treat.
What the research shows
women aged 50 to 79 had pain from the tendons on the side of the hip (23.5%), not the hip joint.
Segal et al., Archives of Physical Medicine and Rehabilitation, 2007of patients with hip arthritis felt pain below the knee — hip pain often travels.
Khan et al., Annals of the Royal College of Surgeons of England, 2004Because it is honest, and because you will find out eventually anyway.
The treatments below are not all covered by every plan, and which ones are open to you depends on who insures you. That is not a judgement about which is best for your joint — it is a constraint we work inside, and we would rather you heard it from us at the start than discovered it at the billing desk.
We will tell you what your plan covers before you commit to anything.
What applies to you depends on what we found, and on what your plan will pay for. Both of those are discussed with you before anything is booked.
An option for patients on Medicare, and for patients being treated under a letter of protection after an injury. →
If you have already had surgery on it. A great many of the joints we see have already been operated on, and the operation did not fix the pain. When that happens the reason is usually one of two, and they are the same two that apply to pain after spine surgery:
The diagnosis was wrong. The operation may have been performed perfectly well on a finding that was never what was hurting you. In that case it was never going to work, and no amount of time or therapy afterwards was going to change that.
Or the pain is now coming from the surgery itself. A different situation, with its own answers.
Either way, the first job is not another procedure. It is finding out which of the two it is — which is the same thing we would have done before the first operation.
The rest of what we do. Physical therapy — some joints need it more than they need anything we can inject, and we will say so. Surgical consultation — some need a surgeon, and when that is the answer we make the referral rather than treating around it. Managing your medications — part of looking after you, alongside the rest, not the plan on its own.
Your first visit is a consultation. We go through what has and has not worked, your medications and your imaging, and plan the steps toward a correct diagnosis.